
If anyone wants to look into the history of "Hypoadrenia" a bit more, there is this paper from 1999:
Hypoadrenia or "a bit of Addison's disease". by R B Tattersall
Adrenocortical Hormone Abnormalities in Men with CP/CPPS
-
webslave

- Maintenance

- Posts: 11432
- Joined: Wed Oct 30, 2002 3:18 pm
- Location: Please give your location so we can help better
Re: Adrenocortical Hormone Abnormalities in Men with CP/CPPS
Good News! The great ProstaQ is BACK at last! You must try it.
| HAS THIS SITE HELPED YOU? Say Thanks by donating. Keep the Forum alive on the Internet! PayPal link at end of page ↓ Contact me at support at ucpps.men |  |
-
Clay
- Veteran

- Posts: 168
- Joined: Mon Sep 25, 2006 3:46 am
- Location: Redmond WA, USA
Re: Adrenocortical Hormone Abnormalities in Men with CP/CPPS
At 6'1" tall, I don't show any signs of CAH, but I have a sister who was operated on in about 1960 for genital abnormality. I was told it was 'just cosmetic, so she could have normal sex, but she would never have children.' Reading all this stuff gave me goose bumps. Congenital adrenal problems are in my family.
I am not a doctor too!
Age 64, sudden onset 5/06 during bout of flu, colitis, lung and liver problems. Pain in penis, then moved to rectum. No urinary symptoms. Use Lyrica, Elavil, paxil, Xanax, morphine, vicodin, relaxation, pads for sitting, 100+ PT sessions. Sensitive to gluten, milk protein, soy. I have CFS, anxiety, GERD, Barrett's, colitis, kidney stones, one of which referred pain to penis.
Age 64, sudden onset 5/06 during bout of flu, colitis, lung and liver problems. Pain in penis, then moved to rectum. No urinary symptoms. Use Lyrica, Elavil, paxil, Xanax, morphine, vicodin, relaxation, pads for sitting, 100+ PT sessions. Sensitive to gluten, milk protein, soy. I have CFS, anxiety, GERD, Barrett's, colitis, kidney stones, one of which referred pain to penis.
-
graeme

- Old Hand

- Posts: 452
- Joined: Fri Jun 17, 2005 3:42 pm
- Location: Birmingham uk
Re: Adrenocortical Hormone Abnormalities in Men with CP/CPPS
Brothers, sisters, even twins, and that's just on this forum. There are family links who knows how far back it could go? Would any of us know if our great great great uncle Bill suffered 
Age:33 | Onset Age:19 | Symptoms:burning urethra, deep sore stinging around the perineum, dribbling | Helped By:when flare starts deep relaxing over a toilet to let out dribbling urine, hot bath, rubbing a heat cream on the perineum, Tens with a pad on the perineum, running, medication (solpadol) for pain. Current treatment: PT. | Worsened By:sitting, stressing over it, ejaculation, sometimes alcohol but I risk it. Been feeling a lot better last 6 months about 85% with a few flares lasting about 5 days. No longer having PT. Stretching every other night and I believe time is also a big factor for me
-
webslave
- Maintenance
- Posts: 11432
- Joined: Wed Oct 30, 2002 3:18 pm
- Location: Please give your location so we can help better
Re: Adrenocortical Hormone Abnormalities in Men with CP/CPPS
It would be fantastic if the cause of this could be isolated as a simple enzyme deficiency, but I urge readers not to get their hopes up. This needs to be confirmed, and then we need to see patients helped by the drug that fixes this (dexamethasone I believe, a powerful steroid, and that I am not thrilled about).
Good News! The great ProstaQ is BACK at last! You must try it.
| HAS THIS SITE HELPED YOU? Say Thanks by donating. Keep the Forum alive on the Internet! PayPal link at end of page ↓ Contact me at support at ucpps.men | |
-
boulder
- Experienced

- Posts: 122
- Joined: Wed Nov 29, 2006 8:52 am
Re: Adrenocortical Hormone Abnormalities in Men with CP/CPPS
First, many, many thanks to Dr. Dimitrakov for sharing his time and expertise on this forum!
There's one simple thing I'm not understanding: If CPPS is related to stress and the stress response, shouldn't we have elevated cortisol levels? Or does chronic stress lower cortisol levels (i.e. we've used it up/burned out the stress response system)?YES, low cortisol levels ARE the initial stimulus which sets the system in motion.
Age: 36 | Onset Age: 29 (Summer 2005) Main Symptoms (all intermittent): penile/anal/rectal/perineum pain/numbness/tingling/coldness, LUTS, ED | Helped By: duloxetine (Cymbalta), topical benzocaine, occasional benzodiazepines, hot weather, hot baths, understanding friends & family, pushing myself to be more sociable and active, psychotherapy (mostly CBT), diaphragmatic breathing, relaxation, meditation (concentration and mindfulness), adequate sleep | Worsened By: cold weather, stress, inadequate sleep, prolonged sitting or standing in place, walking uphill, heavy exercise, erection/ejaculation (sometimes)
Last But Not Least: I am not a medical/health professional of any kind. This is not medical advice.
Last But Not Least: I am not a medical/health professional of any kind. This is not medical advice.
-
boulder
- Experienced
- Posts: 122
- Joined: Wed Nov 29, 2006 8:52 am
Re: Adrenocortical Hormone Abnormalities in Men with CP/CPPS
I may have just answered my own question (or rather, Webslave did, by putting this viewtopic.php?f=37&t=5335&st=0&sk=t&sd=a#p28979 together, which led me to this http://www.ncbi.nlm.nih.gov/sites/entre ... t=citation ):
So, if I understand correctly, this "allostatic overload" is a kind of burnout of the stress response system due to chronic stress, and it leaves us with lower cortisol levels? Thanks to Webslave and everyone else taking the time to figure this out!hypocortisolism may occur after a prolonged period of hyperactivity of the hypothalamic-pituitary-adrenal axis due to chronic stress
Age: 36 | Onset Age: 29 (Summer 2005) Main Symptoms (all intermittent): penile/anal/rectal/perineum pain/numbness/tingling/coldness, LUTS, ED | Helped By: duloxetine (Cymbalta), topical benzocaine, occasional benzodiazepines, hot weather, hot baths, understanding friends & family, pushing myself to be more sociable and active, psychotherapy (mostly CBT), diaphragmatic breathing, relaxation, meditation (concentration and mindfulness), adequate sleep | Worsened By: cold weather, stress, inadequate sleep, prolonged sitting or standing in place, walking uphill, heavy exercise, erection/ejaculation (sometimes)
Last But Not Least: I am not a medical/health professional of any kind. This is not medical advice.
Last But Not Least: I am not a medical/health professional of any kind. This is not medical advice.
-
webslave
- Maintenance
- Posts: 11432
- Joined: Wed Oct 30, 2002 3:18 pm
- Location: Please give your location so we can help better
Re: Adrenocortical Hormone Abnormalities in Men with CP/CPPS
Well, that's what I thought may be happening, but I think Dr Dimitrakov is saying that quite apart from stress, there is an actual biochemical defect in this patient group, an enzyme deficiency that leads to a shortage of cortisol.
Good News! The great ProstaQ is BACK at last! You must try it.
| HAS THIS SITE HELPED YOU? Say Thanks by donating. Keep the Forum alive on the Internet! PayPal link at end of page ↓ Contact me at support at ucpps.men | |
-
carld

- Retired Mod

- Posts: 1554
- Joined: Mon Aug 21, 2006 11:49 pm
- Location: Newbury Park
Re: Adrenocortical Hormone Abnormalities in Men with CP/CPPS
Dr. D,cholesterol from diet is used in the adrenal gland to produce aldosterone, cortisol and sex steroids (testosterone and dehydrotestosterone). These are three separate pathways that are related by virtue of common enzymes (e.g., CYP21A2)
Would the use of statin drugs like Zocor/vytorin over a long period of time to treat high levels of cholesterol be an issue here with effecting aldosterone, cortisol and sex steroids? Thus kick starting this abnormality. I have been on statins for congenital high cholesterol for nearly 10 years. Since I was 28 years old....
Regards, Carl...You ROCK!!!

Last edited by carld on Wed Mar 12, 2008 2:05 pm, edited 1 time in total.
I am not a medical doctor. Please fill out your signature (click here) ☼ ☼ My Starter List for new members
I encourage anxiety prone UCPPS people to consider L-Theanine
Age, 44 onset age 37 Feb 2006 Freq. need to urinate. Sensation of having to urinate soon after going. Perineum discomfort/burning/tightness, pubic area discomfort @ times,poor urine stream, post urine dripping/spray. All symptoms have improved with my protocol. At the worst I give it a 1 to 2 on irritation and discomfort and frequency. Helps: Elavil 5mg for anxiety and mast cell protection, (will only take it as needed) self internal PT as needed, stretching, walking, stairmaster cardio workout and light weights, reducing stress, moment to moment relaxation, deep breathing relaxation and using a Theracane. Makes worse: sitting for long periods, stress, over focusing on it. Currently 95%-98% recovered. Stay positive, relaxed and control your anxiety.
-
neis
- Intermediate Member

- Posts: 99
- Joined: Tue Jan 08, 2008 9:52 pm
Re: Adrenocortical Hormone Abnormalities in Men with CP/CPPS
How about characteristics polar opposite to those stated? Very short as a child, and tall as an adult. Very late puberty(19), and beard growth(25).
Age: | Onset Age: | Symptoms: | Helped By: | Worsened By:
-
J Dimitrakov

- Urologist

- Posts: 326
- Joined: Wed Oct 30, 2002 4:59 pm
- Location: Boston, MA
Re: Adrenocortical Hormone Abnormalities in Men with CP/CPPS
I could not agree more. As I said in my first post:webslave wrote:It would be fantastic if the cause of this could be isolated as a simple enzyme deficiency, but I urge readers not to get their hopes up. This needs to be confirmed, and then we need to see patients helped by the drug that fixes this (dexamethasone I believe, a powerful steroid, and that I am not thrilled about).
- the results are exciting but preliminary;
- need replication on a larger patient sample;
- need more detailed characterization of the enzyme abnormality we identified at the level of the genome;
All that being said, again, if we had even ONE good biomarker such as the one we identified that would be a HUGE breakthrough in the field of CPPS. As most of you are aware, the field as a whole has been quite reluctant in terms of replication and people usually take it quite personally if someone even DARES to think about replicating their findings: something which is the RULE in the field of cancer and HIV biomarkers for example.
For now, we are continuing our studies and will soon be reporting in more detail our findings.
Best,
JD
This communication provides general information, and is not a substitute for face-to-face medical care. A doctor-patient relationship should not be assumed by the reader.
Jordan Dimitrakov, M.D., Ph.D.
Jordan Dimitrakov, M.D., Ph.D.
-
J Dimitrakov
- Urologist
- Posts: 326
- Joined: Wed Oct 30, 2002 4:59 pm
- Location: Boston, MA
Re: Adrenocortical Hormone Abnormalities in Men with CP/CPPS
Boulder,boulder wrote:First, many, many thanks to Dr. Dimitrakov for sharing his time and expertise on this forum!
There's one simple thing I'm not understanding: If CPPS is related to stress and the stress response, shouldn't we have elevated cortisol levels? Or does chronic stress lower cortisol levels (i.e. we've used it up/burned out the stress response system)?YES, low cortisol levels ARE the initial stimulus which sets the system in motion.
Thanks for your comment. The present study looked at cortisol levels at ONE SPECIFIC POINT IN TIME. This is one of the limitations of the study which we discuss in the comment section of our paper. Unfortunately, you can't do every single thing in a single paper and we are looking at cortisol levels prospectively (i.e. over time).
You are correct that under physiologic conditions, stress would trigger release of cortisol from the adrenal. In this situation, the high cortisol levels are a protective reaction. You are correct (again) that with time cortisol levels would burn out and low cortisol levels are frequently observed in people with PBS/IC, fibromyalgia, chronic fatigue syndrome. We have made a similar observation in a separate study which I presented at the AUA in 2006 and which is under peer review for publication (you can search for our allostatic overload abstract).
Hope this is helpful - let me know if there are any other questions
Best,
JD
This communication provides general information, and is not a substitute for face-to-face medical care. A doctor-patient relationship should not be assumed by the reader.
Jordan Dimitrakov, M.D., Ph.D.
Jordan Dimitrakov, M.D., Ph.D.
-
J Dimitrakov
- Urologist
- Posts: 326
- Joined: Wed Oct 30, 2002 4:59 pm
- Location: Boston, MA
Re: Adrenocortical Hormone Abnormalities in Men with CP/CPPS
Yes, it looks like, at least in the group of CPPS patients we studied, there is a (most likely) genetic predisposition - a mutation in the enzyme CYP21A2. This predisposition, depending on the specific type of mutation, appears to be quite common and can range from no symptoms to mild symptoms to full-blown CAH.webslave wrote:Well, that's what I thought may be happening, but I think Dr Dimitrakov is saying that quite apart from stress, there is an actual biochemical defect in this patient group, an enzyme deficiency that leads to a shortage of cortisol.
Interestingly, the predisposition could remain silent forever or be triggered, most likely by stress (similar to the two-hit hypothesis of cancer). It's quite intriguing that CYP21A2 levels (and its expression at the level of mRNA and protein) are highest in muscles and brain (nerve tissue). Therefore, a deficiency in the enzyme would results in symptoms from the muscles and the nerves
Best,
JD
This communication provides general information, and is not a substitute for face-to-face medical care. A doctor-patient relationship should not be assumed by the reader.
Jordan Dimitrakov, M.D., Ph.D.
Jordan Dimitrakov, M.D., Ph.D.
-
J Dimitrakov
- Urologist
- Posts: 326
- Joined: Wed Oct 30, 2002 4:59 pm
- Location: Boston, MA
Re: Adrenocortical Hormone Abnormalities in Men with CP/CPPS
Carl,carld wrote:Dr. D,cholesterol from diet is used in the adrenal gland to produce aldosterone, cortisol and sex steroids (testosterone and dehydrotestosterone). These are three separate pathways that are related by virtue of common enzymes (e.g., CYP21A2)
Would the use of statin drugs like Zocor/vytorin over a long period of time to treat high levels of cholesterol be an issue here with effecting aldosterone, cortisol and sex steroids? This kick starting this abnormality. I have been on statins for congenital high cholesterol for nearly 10 years. Since I was 28 years old....
Regards, Carl...You ROCK!!!
Thanks for this interesting question. None of the men in our series was taking a statin but this is a good research question for the future.
The technique we used is 10-100 fold more sensitive than conventional ELISA-based assays, so, it would be interesting to look at the group of patients you suggested. For now, here are two interesting abstracts from PubMed:
Published Online, 2 January 2007, http://www.theannals.com, DOI 10.1345/aph.1H444.
The Annals of Pharmacotherapy: Vol. 41, No. 1, pp. 138-142. DOI 10.1345/aph.1H444
Probable Statin-Induced Testicular Pain
Sunny A Linnebur, PharmD
Assistant Professor, Department of Clinical Pharmacy, University of Colorado at Denver and Health Sciences Center, Denver, CO
William H Hiatt, MD
Professor, Department of Medicine, University of Colorado at Denver and Health Sciences Center
Reprints: Dr. Linnebur, Department of Clinical Pharmacy, University of Colorado at Denver and Health Sciences Center, 4200 E. Ninth Ave., Box C238, Denver, CO 80262, fax 303/315-4630, [email protected]
OBJECTIVE: To describe a case of a patient experiencing testicular pain on 3 occasions after taking 3 different statins.
CASE SUMMARY: A 54-year-old man with hyperlipidemia was started on lovastatin therapy. His other medications included aspirin, levothyroxine, buspirone, and atenolol. Seven months after starting lovastatin, the patient experienced testicular discomfort that resolved upon discontinuation of the drug. Afterward, he started simvastatin and again experienced testicular discomfort. The simvastatin was changed to atorvastatin, and the pain resolved. However, 3 months after starting atorvastatin, the patient developed testicular pain, which resolved after the drug was stopped. During each of the episodes, the patient's pain increased when he was sitting, driving, or wearing tight clothing. The Naranjo probability scale indicates that statins probably caused the patient's pain.
DISCUSSION: Testicular pain is rarely caused by medications. Product labeling for statins does not list urinary adverse events as common. However, labeling for atorvastatin and pravastatin lists rare urologic adverse effects. A literature search did not reveal any previously reported cases of testicular adverse effects from statins. However, statins have been shown to inhibit cholesterol synthesis in the testis. Some data indicate that statins reduce serum testosterone concentrations, but other data indicate that statins have no effect on sex hormones or spermatogenesis. Data are also available indicating that aspirin might affect testosterone concentrations and testicular function. It is difficult to know whether either of the above hormonal mechanisms was associated with our patient's testicular discomfort, but the time course and challenge/rechallenge aspects of the case suggest that the statins were the cause.
CONCLUSIONS: Urologic adverse effects of statins rarely occur but should not be overlooked by medical providers.
Key Words: hydroxymethylglutaryl coenzyme A reductase inhibitors, testicular diseases
Published Online, January 2, 2007. http://www.theannals.com, DOI 10.1345/aph.1H444
-----------------------------------------------------------------------------------------------
Metabolism. 2000 Sep;49(9):1234-8.
Effects of high-dose simvastatin on adrenal and gonadal steroidogenesis in men with hypercholesterolemia.Dobs AS, Schrott H, Davidson MH, Bays H, Stein EA, Kush D, Wu M, Mitchel Y, Illingworth RD.
Department of Medicine, The Johns Hopkins University School of Medicine, Baltimore, MD, USA.
In view of the role of both the de novo biosynthesis and receptor-mediated uptake of cholesterol for normal steroidogenesis, we evaluated whether extending the therapeutic dose of the hepatic hydroxymethyl glutaryl coenzyme A (HMG-CoA) reductase inhibitor, simvastatin, to 80 mg/d would affect adrenal and gonadal steroid synthesis in men with hypercholesterolemia. To evaluate this question, we enrolled men into a multicenter randomized, placebo-controlled study lasting 12 weeks. Men with serum low-density lipoprotein cholesterol (LDL-C) more than 145 mg/dL after 6 weeks of a lipid-lowering diet were randomized to 80 mg simvastatin or placebo. Half of the subjects were asked to undergo a 6-hour infusion of corticotropin (ACTH) to evaluate cortisol synthesis, and the entire cohort received a human chorionic gonadotropin (hCG) stimulation test to assess gonadal hormone secretion using pooled serum samples taken 15 minutes apart. A total of 81 men (age, 45 +/- 11 years; 93% Caucasian) with baseline serum LDL-C of 197 mg/dL (placebo, n = 39) and 184 mg/dL (simvastatin 80 mg, n = 42) completed the study. After 12 weeks, serum LDL-C, triglycerides, and high-density lipoprotein cholesterol (HDL-C) in the simvastatin group changed by -43%, -25%, and 8%, respectively (all P < .001). The basal cortisol level and the peak serum cortisol and area under the curve response to the 6-hour ACTH infusion were comparable between the two treatment groups at baseline and after 12 weeks. The pooled total testosterone level at baseline was 541 and 513 ng/dL in the placebo and simvastatin-treated groups, respectively, which declined to 536 +/- 20.5 ng/dL (-1.5%) and 474 +/- 30.4 ng/dL (-13.6%, P = .09) after treatment (mean +/- SD). The pooled free testosterone declined by 6.3% in the simvastatin group, versus a 4.9% increase in the placebo group (P = .588), while pooled bioavailable testosterone declined 10.2% in the simvastatin group and increased 1.4% in the placebo group (P = .035). There were no changes in serum gonadotropin levels or sex hormone-binding globulin (SHBG). After administration of hCG, there were no differences in the peak total pooled testosterone level before or after 12 weeks of treatment. Simvastatin 80 mg was well tolerated compared with placebo. In conclusion, basal and stimulated cortisol production was unaffected by the use of simvastatin 80 mg versus placebo. As reported with other statins and cholestyramine, there were small declines in the simvastatin-treated group for pooled total, free, and bioavailable testosterone after 12 weeks, although there was no compensatory increase in serum follicle-stimulating hormone (FSH) or luteinizing hormone (LH) levels.
PMID: 11016911 [PubMed - indexed for MEDLINE]
-------------------------------------
Best,
JD
This communication provides general information, and is not a substitute for face-to-face medical care. A doctor-patient relationship should not be assumed by the reader.
Jordan Dimitrakov, M.D., Ph.D.
Jordan Dimitrakov, M.D., Ph.D.
-
boulder
- Experienced
- Posts: 122
- Joined: Wed Nov 29, 2006 8:52 am
Re: Adrenocortical Hormone Abnormalities in Men with CP/CPPS
Tremendously so, thank you again! I must say, direct engagement on the part of medical experts like yourself with this patient community is genuinely inspiring.Hope this is helpful
Fascinating indeed! Life events affecting gene expression, this is really hot stuff- Definitely sounds like a promising avenue for further research. Best of luck to you, Dr. Dimitrakov, and hats off!Interestingly, the predisposition could remain silent forever or be triggered, most likely by stress (similar to the two-hit hypothesis of cancer). It's quite intriguing that CYP21A2 levels (and its expression at the level of mRNA and protein) are highest in muscles and brain (nerve tissue). Therefore, a deficiency in the enzyme would results in symptoms from the muscles and the nerves
Age: 36 | Onset Age: 29 (Summer 2005) Main Symptoms (all intermittent): penile/anal/rectal/perineum pain/numbness/tingling/coldness, LUTS, ED | Helped By: duloxetine (Cymbalta), topical benzocaine, occasional benzodiazepines, hot weather, hot baths, understanding friends & family, pushing myself to be more sociable and active, psychotherapy (mostly CBT), diaphragmatic breathing, relaxation, meditation (concentration and mindfulness), adequate sleep | Worsened By: cold weather, stress, inadequate sleep, prolonged sitting or standing in place, walking uphill, heavy exercise, erection/ejaculation (sometimes)
Last But Not Least: I am not a medical/health professional of any kind. This is not medical advice.
Last But Not Least: I am not a medical/health professional of any kind. This is not medical advice.
-
webslave
- Maintenance
- Posts: 11432
- Joined: Wed Oct 30, 2002 3:18 pm
- Location: Please give your location so we can help better
Re: Adrenocortical Hormone Abnormalities in Men with CP/CPPS
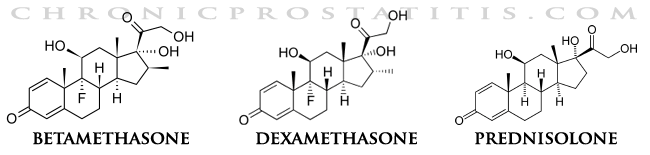
Here is a significant data point that may excite some readers. In 1992, when I was most ill with CPPS, I took a few Celestamine® tablets and had immediate, dramatic relief from almost all symptoms, as I remember. Unfortunately I only had a few of these tablets. I'd picked them up during my peregrinations around the globe and couldn't get them again in the country where I was living at the time. The constituents of Celestamine are, wait for it:webslave wrote:It would be fantastic if the cause of this could be isolated as a simple enzyme deficiency, but I urge readers not to get their hopes up. This needs to be confirmed, and then we need to see patients helped by the drug that fixes this (dexamethasone I believe, a powerful steroid, and that I am not thrilled about).
Betamethasone 0.25mg
Dexchlorpheniramine maleate (H1 block) 2mg
Betamethasone is a form of cortisone (a steroid) that has been modified to enhance its anti-inflammatory effect. It is very similar but not as powerful as dexamethasone. Looking back now, I can't say why I didn't revisit this issue. I've only just remembered it, as a matter of fact.
Years later, trying to recapture this effect, I tried prednisolone but experienced no improvement, in fact I felt generally unwell while taking it. I noticed no improvement in my CPPS symptoms after 2 weeks, but I was taking a minimal dose.
So question for Dr D is: is this consistent? Are prednisolone and betamethasone so different as to account for this?
Data:
------------------------
CELESTAMINE TABS/SYRUP
Main Use:
Acute allergic rhinitis, not responsive to conventional therapy. Steroid responsive dermatological allergies and steroid responsive dermatoses
Active Ingredients:
Betamethasone
Dexchlorpheniramine (H1 block) *
Celestamine Tablets:
0.25mg betamethasone + 2mg dexchlorpheniramine maleate
Celestamine is to be used only as a short term treatment (less than 5 days). Celestamine should only be used in well defined indications. Celestamine should not be mixed with other mixtures. The recommended initial dosage of Celestamine tablets and syrup for adults and children over 12 years is 1 - 2 tablets (or 5ml - 10ml),4 times daily, after meals and at bedtime. The dose should not exceed 8 tablets or 40ml of syrup/day. As improvement occurs, the dosage should be gradually reduced to a maintenance level and discontinued if at all possible.Treatment should not exceed 5 days. A course of treatment should not be repeated within 28 days unless specifically indicated and prescribed by the medical practitioner. Safety in children has not been established
Betamethasone
Mechanism:
As for cortisones. Manipulation of the chemical structure has allowed for enhancement in the anti-inflammatory action.
Indications:
Management of various rheumatic, allergic, dermatological, ocular and other conditions known to be responsive to corticosteroid therapy. The most important of these are : Rheumatoid arthritis, acute rheumatic fever, disseminated lupus erythamatosus, scleroderma, dermatomyositis, bronchial asthma (including status asthmaticus), intractable allergic rhinitis, angioedema, transfusion reactions, drug serum reactions, atopic dermatitis, contact dermatitis, neurodermatitis, allergic eczema, exfoliative dermatitis, urticaria, dermatitis herpatiformis, uveitis, chorioretinitis, sympathetic opthalmia, iritis, iridocyclitis, retinitis centralis, herpes zoster ophthalmicus, optic neuritis, retrobulbar neuritis, bursitis, synovitis, tenosynovitis, idiopathic thrombocytopenic purpura, allergic purpura, adrenogenital syndrome, acute gouty arthritis, pemphigus, ulcerative colitis, nephrotic syndrome, pulmonary emphysema, pulmonary fibrosis, nasal polyps and Bell's palsy.
Contra-Indications:
Hypersensitivity to corticosteroids. Herpes simplex of the eye. Systemic fungal infections. Relative contra-indications ...consider risk against benefit in patients with: Osteoporosis Peptic ulceration Acute or chronic infections Marked emotional instability Tuberculosis
Side-Effects:
See corticosteroids. Sodium and water retention is characteristic with older cortisones, but betamethasone has been found to produce an increase in sodium excretion, normally in patients receiving daily doses well above the recommended therapeutic range. Potassium loss does not appear to occur.
Precautions:
Monitor electrolyte levels occasionally. Infection should be ruled out before corticosteroid therapy is instituted or appropriate antibiotics should be given concurrently. In individuals exposed to the active phase of chickenpox or other exanthematous disease, it may be desirable to temporarily reduce or discontinue corticosteroid therapy. Patients on prolonged therapy should never stop treatment abruptly... taper down dosage gradually. Monitor eye function with long term use ...prolonged use may produce posterior subcapsular cataracts and glaucoma with possible damage to the optic nerves and may enhance the establishment of secondary ocular infections due to fungi or viruses. Immunisation procedures such as for smallpox, should not be undertaken in patients receiving corticosteroids. Patients with latent tuberculosis receiving corticosteroids should be closely observed and should receive chemoprophylaxis. There is an enhanced effect of corticosteroids in patients with hypothyroidism or with cirrhosis. Psychic derangements may appear with corticosteroid therapy ...caution in patients with emotional instability or psychotic tendencies. Caution in non-specific colitis, if there is a probability of impending perforation, abscess or pyogenic infections, in diverticulitis, in fresh intestinal anastomoses, with renal insufficiency, with hypertension and with myasthenia gravis. Caution in children and infants due to effect on growth development.
Good News! The great ProstaQ is BACK at last! You must try it.
| HAS THIS SITE HELPED YOU? Say Thanks by donating. Keep the Forum alive on the Internet! PayPal link at end of page ↓ Contact me at support at ucpps.men | |